Evidence

The research is limited. It isn’t empty.

The record includes human studies, historical medical literature, laboratory chemistry, animal work, practitioner reports, safety cases, and adjacent research on coffee, bile, glutathione, and the liver.

Add Coffee and Enemas as a preferred source on Google

The concise answer

What does human research actually show?

Human research has demonstrated rectal caffeine absorption, reported improved constipation in an uncontrolled 42-patient series, and studied coffee enemas for bowel preparation before capsule endoscopy. One low-dose Thai protocol didn’t improve selected serum antioxidant markers. No single study settles every proposed or reported effect.

Author: Scott A. Wilson · Updated: September 21, 2026 · Source distinctions and disclosure

Established in the tested settingSuggestive or adjacent evidenceReported experienceStill unmeasured

The revised book

Read the discussion, or find a study quickly.

Scott describes gathering more than eighty papers and historical source documents for the revised manuscript, including translated international material. Chapter 9 brings the findings together; Evidence at a Glance provides a quick reference to what the studies tested, found, and left unanswered.

Explore Chapter 9 → Evidence at a Glance →

01

Rectal caffeine absorption

A randomized crossover study in eleven healthy men demonstrated caffeine absorption from a 4-gram, 500-millilitre coffee enema retained for ten minutes. Systemic caffeine exposure was lower than after the tested oral coffee.

Human pharmacokinetic study

Read the study →

02

Selected antioxidant markers

A small study using the same low-dose preparation didn’t demonstrate improvement in the serum glutathione, total antioxidant capacity, or malondialdehyde measurements it selected. It didn’t measure bile flow, liver-tissue GST, bowel function, pain, nausea, or subjective relief.

Human intervention study

Read the record →

03

Constipation series

An uncontrolled series of 42 patients reported improved constipation and defecation-frequency scores. With no control group, randomisation, blinding, or objective transit measurement, it remains a signal rather than a definitive trial.

Uncontrolled clinical series · Song, Kim and Lee, 2005

Read the original Korean paper →

04

Capsule-endoscopy preparation

A small pilot studied coffee enemas as part of bowel preparation before small-bowel capsule endoscopy. It concerned visualization and bile clearing, not proof of detoxification or liver treatment.

Human clinical pilot

Read the study →

05

Published safety reports

A systematic review assembled adverse-event case reports but couldn’t calculate incidence. Incident-level reading matters because excessive temperature, frequency, volume, infection risk, mechanical factors, and severe patient vulnerability aren’t the same causal claim.

Case-report review · Son and colleagues, 2020

Read the published review →

Read the safety analysis →

06

Coffee, liver, and glutathione

Animal and oral-coffee research provides relevant biological context involving coffee compounds, glutathione, liver measures, and gallbladder contraction. These studies aren’t human coffee-enema efficacy trials.

Adjacent evidence

Why this research matters to me

I believe coffee enemas have real value as a detoxification practice. Since 1998, I’ve worked on the coffee itself, paid for laboratory testing, read the research, and spoken with thousands of people about their experiences. Those repeated conversations are a substantial part of why I’ve stayed with this work.

The papers give me another way to examine the questions. Some measure what enters the bloodstream. Others look at bowel preparation, symptoms, or particular blood markers. I want the reader to see the actual question behind each result.

Does caffeine enter the bloodstream from a coffee enema?

Yes. Teekachunhatean and colleagues’ 2013 crossover study measured caffeine after oral coffee and after a coffee enema in eleven healthy men. Rectal exposure was lower under that protocol. That answers an absorption question; it doesn’t establish the response to every coffee, concentration, or schedule.

For practical reading, the important point is that avoiding swallowed coffee doesn’t necessarily avoid caffeine exposure. Individual sensitivity belongs in the discussion of preparation and frequency.

Teekachunhatean et al., 2013, ISRN Pharmacology, article 147238. DOI: 10.1155/2013/147238.

Read the frequency guide →

Glutathione and GST: what was actually measured?

Glutathione is a molecule involved in the body’s antioxidant systems. Glutathione S-transferases, often shortened to GST, are enzymes. An increase in one measurement doesn’t automatically establish an increase in the other.

Lam, Sparnins and Wattenberg’s 1982 mouse-feeding research identified coffee compounds associated with increased GST activity. It’s part of the biochemical background, with the species and route kept clear.

In 2003, Esposito and colleagues studied oral coffee in 22 volunteers, with five additional controls. Plasma glutathione increased during the week of coffee consumption and returned to its original level after the coffee-free period. That’s a human finding about drinking coffee, not a measurement of liver GST or rectal administration.

The 2012 Thai coffee-enema study didn’t find the hoped-for changes in its selected serum antioxidant markers. Those results belong in the record. They don’t measure every proposed local, hepatic, or subjective effect.

Original records: Lam, Sparnins and Wattenberg, 1982; Esposito et al., 2003; Teekachunhatean et al., 2012.

What does the constipation research contribute?

Song, Kim and Lee’s 2005 Korean paper followed 42 patients and reported improvement in constipation and defecation-frequency scores. It gives us a clinical observation worth examining. Without a control group, randomisation, or blinding, it can’t establish how much improvement was attributable to coffee rather than the procedure or other influences.

The 2014 capsule-endoscopy pilot asked a different question about preparation and visualisation. Keeping those purposes separate prevents a bowel-preparation result from becoming a claim about liver detoxification.

Song, Kim and Lee, “The Effect of Coffee Enema on Constipation,” 2005, 5(1):31–45; Kim et al., “Coffee Enema for Preparation for Small Bowel Video Capsule Endoscopy: A Pilot Study,” 2014.

What research would move the discussion forward?

A useful study would specify the coffee and preparation, measure the outcome it claims to investigate, and record adverse events alongside benefits. A comparison with a suitable control would help distinguish the effects of coffee from the effects of an enema. Studies of repeated use would also need to document the surrounding diet, fluids, and schedule.

My experience gives me reasons to take the practice seriously. Better research could help explain the benefits people describe and clarify who responds, under what conditions, and why.

Follow the documented history →

Read the safety record and stop conditions →

About this guide

Written by Scott A. Wilson, author of Coffee Enemas: The Evidence, the History, and the Practice and founder of S.A. Wilson’s Gold Roast Coffee. I have a commercial interest in coffee products. The studies linked here are distinguished from my company records and personal experience.

Read the source categories and disclosure →

Honest uncertainty

“There’s no research” is wrong. “Clinically proven detoxification” goes too far.

I believe coffee enemas support detoxification. Has there been a modern human trial that follows the entire proposed process from beginning to end and proves it? No.

That is an evidence gap. It isn’t a negative trial, and it doesn’t erase the history, chemistry, practitioner experience, or reports from the people using the practice.

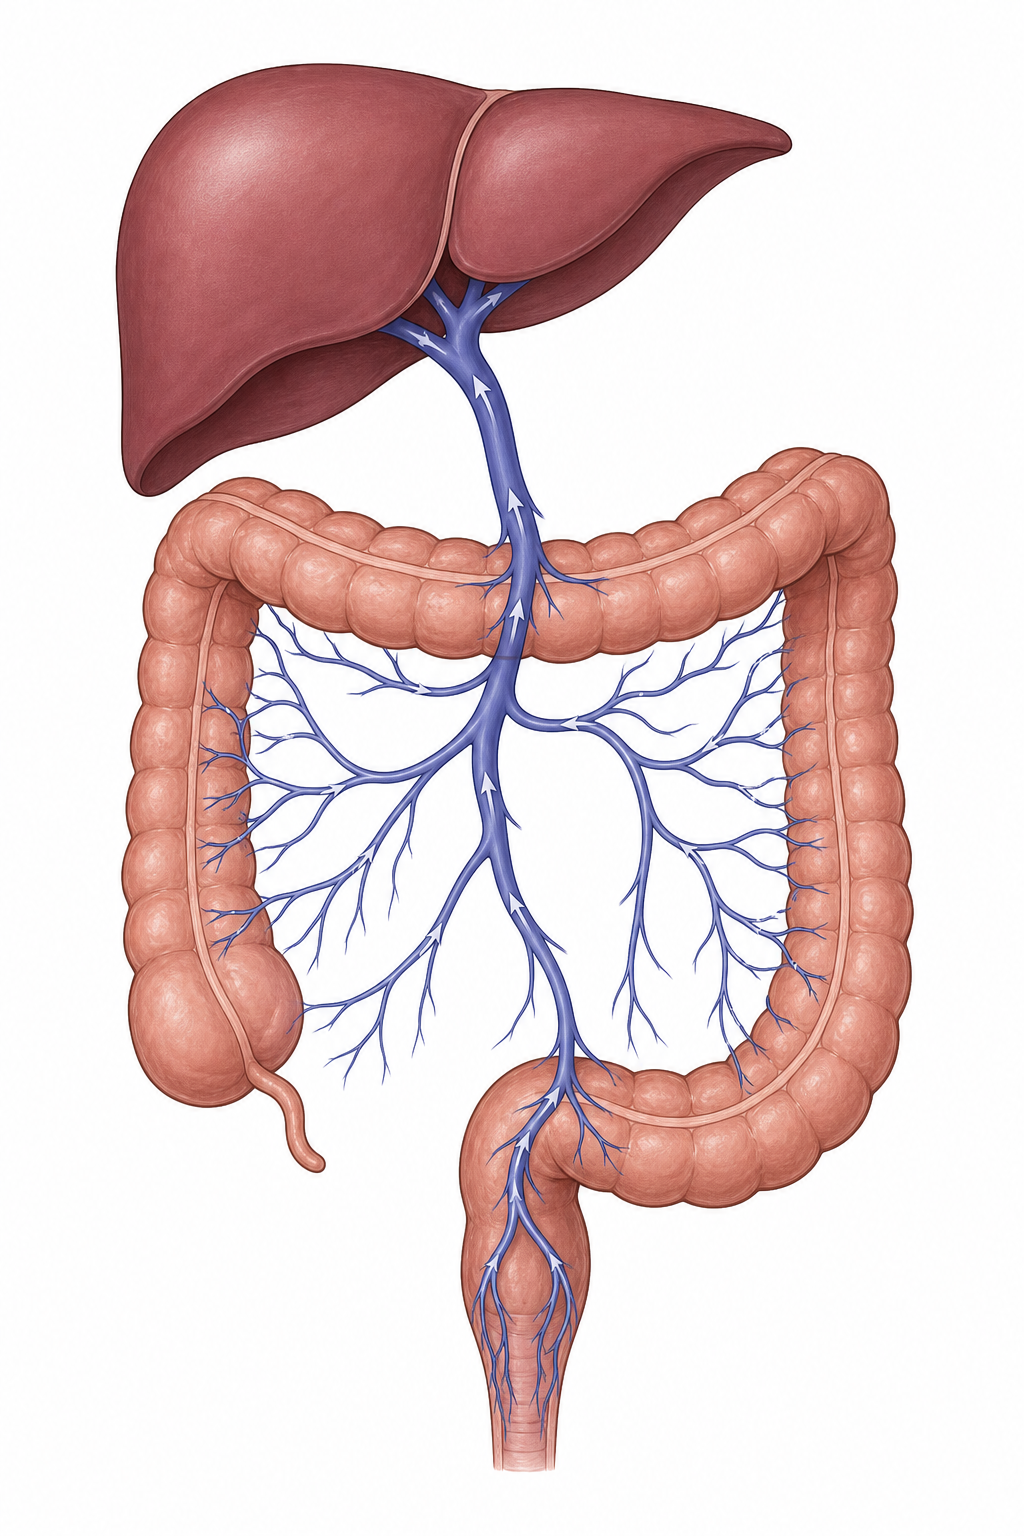
Educational diagram of the colon and portal circulation

Mechanism

The coffee stays in the bowel.

Historical explanations proposed that absorbed compounds travel through venous drainage toward the portal circulation and liver. Modern anatomy supports portal drainage from multiple parts of the large bowel. A complete modern human coffee-enema trial has not directly measured every step of that proposed pathway.

Educational anatomy image. It illustrates the proposed route; it does not depict a measured clinical outcome.

Why the basic method uses the right side →

The complete record

Evidence makes more sense when every source keeps its proper label.

See how the book separates independent research, historical theory, laboratory findings, company records, and direct experience.